Obesity and insulin resistance have a bidirectional relationship. When excess fat, particularly visceral fat, accumulates excessively, the body becomes more likely to respond poorly to insulin. Conversely, insulin resistance forces the pancreas to secrete more insulin to maintain stable blood glucose levels. Over time, this can increase the risk of prediabetes, type 2 diabetes, fatty liver disease, dyslipidemia and metabolic syndrome.
Not all people with obesity have insulin resistance to the same degree. The risk is often higher in those with abdominal obesity, physical inactivity, fatty liver disease, elevated triglycerides, a family history of type 2 diabetes, a history of gestational diabetes or polycystic ovary syndrome, now increasingly discussed in relation to broader metabolic and endocrine dysfunction and previously commonly referred to as PCOS.
Quick answer: Obesity can cause insulin resistance because visceral fat and excess adipose tissue increase chronic inflammation, free fatty acids and impaired insulin signaling in the liver, skeletal muscle and adipose tissue. Insulin resistance often has no obvious symptoms, but it may be suggested by abdominal obesity, elevated blood glucose, high HbA1c, increased triglycerides, fatty liver disease, acanthosis nigricans in the neck or underarm areas, or PMOS/PCOS. Weight management, reduction of visceral fat, a balanced diet, regular physical activity and adequate sleep may help improve insulin sensitivity in many cases.
Professional medical consultation: Nguyen Thi Nhu Quynh, MD, MSc, Resident Physician - Department of Endocrinology, Hong Ngoc Phuc Truong Minh General Hospital.
Medical disclaimer: This article is for informational purposes only and is not a substitute for medical diagnosis or treatment. Patients should not order insulin testing, interpret HOMA-IR results, or use metformin, GLP-1 receptor agonists, weight-loss medications or blood glucose-lowering medications without a physician’s indication. If excessive thirst, frequent urination, rapid weight loss, extreme fatigue, persistent vomiting, altered consciousness, chest pain or shortness of breath occurs, patients should seek medical care or emergency treatment promptly.
Article overview
What is obesity-related insulin resistance?
Insulin resistance is a condition in which cells in skeletal muscle, the liver and adipose tissue respond poorly to insulin. Insulin helps glucose move from the bloodstream into cells to be used for energy. When the body becomes insulin resistant, the pancreas has to produce more insulin to keep blood glucose from rising too high.
In people with obesity, particularly abdominal obesity, insulin resistance is often associated with visceral fat, dysfunctional adipose tissue, fatty liver disease and low-grade chronic inflammation. In the early stages, blood glucose may remain within the normal range because the pancreas increases insulin secretion to compensate. However, if this condition persists, pancreatic beta-cell function may gradually decline, increasing the risk of prediabetes and type 2 diabetes.
In brief: Obesity-related insulin resistance is a condition in which excess fat, especially visceral fat, makes the body less responsive to insulin. As a result, the pancreas must produce more insulin to control blood glucose, which over time can lead to metabolic disorders.
Why does obesity increase the risk of insulin resistance?
Visceral fat disrupts insulin signaling
Visceral fat is located deep within the abdominal cavity, close to the liver and other metabolic organs. When visceral fat increases, the amount of free fatty acids and inflammatory mediators delivered to the liver may also rise, making the liver and skeletal muscle less responsive to insulin.
People with a large waist circumference, even when their BMI is not very high, may still have insulin resistance. Therefore, waist circumference and visceral fat are just as important as body weight.
In Asian populations, a waist circumference of 90 cm or greater in men and 80 cm or greater in women is commonly considered a threshold that warrants attention for abdominal obesity and metabolic risk.
Excess adipose tissue causes low-grade chronic inflammation
Adipose tissue is not merely a site for energy storage. When adipose tissue becomes enlarged, immune cells can infiltrate it and trigger low-grade chronic inflammation. This process impairs insulin signaling.
Insulin resistance is not simply caused by “eating too much sugar.” It is a complex metabolic disorder involving adipose tissue, inflammation, the liver, skeletal muscle, sleep, physical activity and genetic factors.
Fatty liver disease worsens insulin resistance
The liver plays a central role in blood glucose regulation and fat metabolism. When fat accumulates in the liver, the liver may continue producing glucose even in the presence of insulin, making blood glucose more likely to rise. Fatty liver disease and insulin resistance often form a metabolic vicious cycle.
People with obesity who also have fatty liver disease, elevated liver enzymes or high triglycerides should have their blood glucose and HbA1c checked, as their risk of prediabetes or type 2 diabetes may be increased.
Physical inactivity reduces glucose utilization by skeletal muscle
Skeletal muscle is one of the main sites of glucose utilization after meals. With physical inactivity, low muscle mass or prolonged sitting, skeletal muscle uses glucose less effectively, forcing insulin to work harder to move glucose into cells.
Exercise, particularly regular physical activity and strength training, helps skeletal muscle use glucose more effectively and improves insulin sensitivity.

Poor sleep and stress make blood glucose more difficult to control
Sleep deprivation, staying up late and prolonged stress can affect hunger and satiety hormones, cortisol levels, appetite and blood glucose control. In people with obesity, these factors may worsen insulin resistance.
Improving insulin resistance is not simply about eating less. Patients also need to get adequate sleep, reduce stress, limit late-night eating and maintain a stable daily routine.
Signs of insulin resistance in people with obesity
Insulin resistance often has no specific symptoms. Many people only discover it when tests show abnormal blood glucose, HbA1c, blood insulin or lipid levels.
Abdominal obesity and large waist circumference
Abdominal obesity is a sign that may suggest increased visceral fat, a factor closely associated with insulin resistance. People with a large waist circumference are more likely to also have fatty liver disease, elevated triglycerides and abnormal blood glucose.
In Asian populations, a waist circumference of 90 cm or greater in men and 80 cm or greater in women is a threshold that warrants attention for abdominal obesity or central obesity.

Elevated fasting blood glucose or HbA1c
In the early stages, blood glucose may remain normal because the pancreas increases insulin secretion to compensate. When this compensatory capacity declines, fasting blood glucose or HbA1c begins to rise, suggesting prediabetes or type 2 diabetes.
People with obesity should have fasting blood glucose and HbA1c checked regularly, especially if they have a family history of diabetes, fatty liver disease or elevated triglycerides.
Sleepiness and fatigue after a high-carbohydrate meal
Some people may feel tired, sleepy, hungry again quickly or crave sweets after a high-carbohydrate meal. This is not a diagnostic sign of insulin resistance, but it may suggest blood glucose fluctuations and an inappropriate meal composition.
If symptoms recur, patients should record their meals, check blood glucose when necessary and adjust carbohydrate quality under professional guidance.
Acanthosis nigricans on the neck, underarms or groin
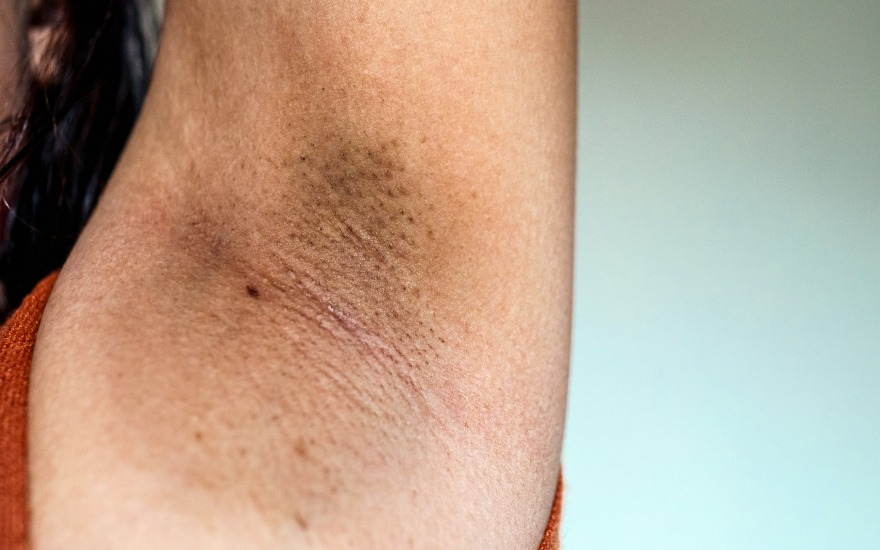
Acanthosis nigricans is a condition in which the skin becomes darker, thicker and slightly velvety, commonly appearing on the neck, underarms, groin or skin folds. This sign may be associated with persistently elevated insulin levels.
If the skin around the neck or underarms becomes dark and thick, especially when accompanied by abdominal obesity, abnormal blood glucose or menstrual irregularities, patients should see an endocrinologist to assess blood glucose, insulin levels and the risk of PMOS/PCOS or diabetes.
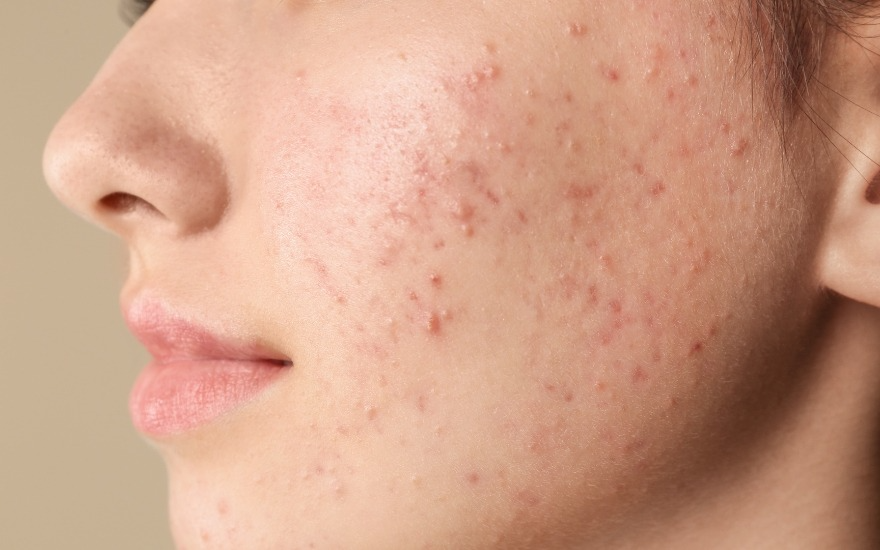
Menstrual irregularities, acne and hirsutism in women
Insulin resistance may be associated with polycystic ovary metabolic and endocrine syndrome, or PMOS, previously commonly referred to as PCOS. Patients may experience infrequent menstruation, amenorrhea, acne, hirsutism, male-pattern hair loss or difficulty conceiving.
Women with obesity who have these signs should seek evaluation by an endocrinologist or obstetrician-gynecologist. They should not rely solely on self-directed weight loss or use menstrual-regulating medications without medical guidance.
Fatty liver disease and elevated triglycerides
Fatty liver disease and dyslipidemia often occur alongside insulin resistance. This is why many people discover insulin resistance during evaluation for elevated liver enzymes or abnormal blood lipid levels.
If fatty liver disease, elevated triglycerides or low HDL cholesterol is already present, blood glucose, HbA1c and metabolic syndrome risk should also be assessed.
Is obesity-related insulin resistance dangerous?
Yes. Insulin resistance is a key underlying mechanism of many metabolic disorders. If left uncontrolled, patients may progress to several chronic diseases.
Prediabetes and type 2 diabetes
When the body becomes insulin resistant, the pancreas must produce more insulin to maintain stable blood glucose levels. Over time, insulin secretion may decline, causing blood glucose to rise gradually.
Early detection of insulin resistance gives patients the opportunity to intervene before it progresses to type 2 diabetes.
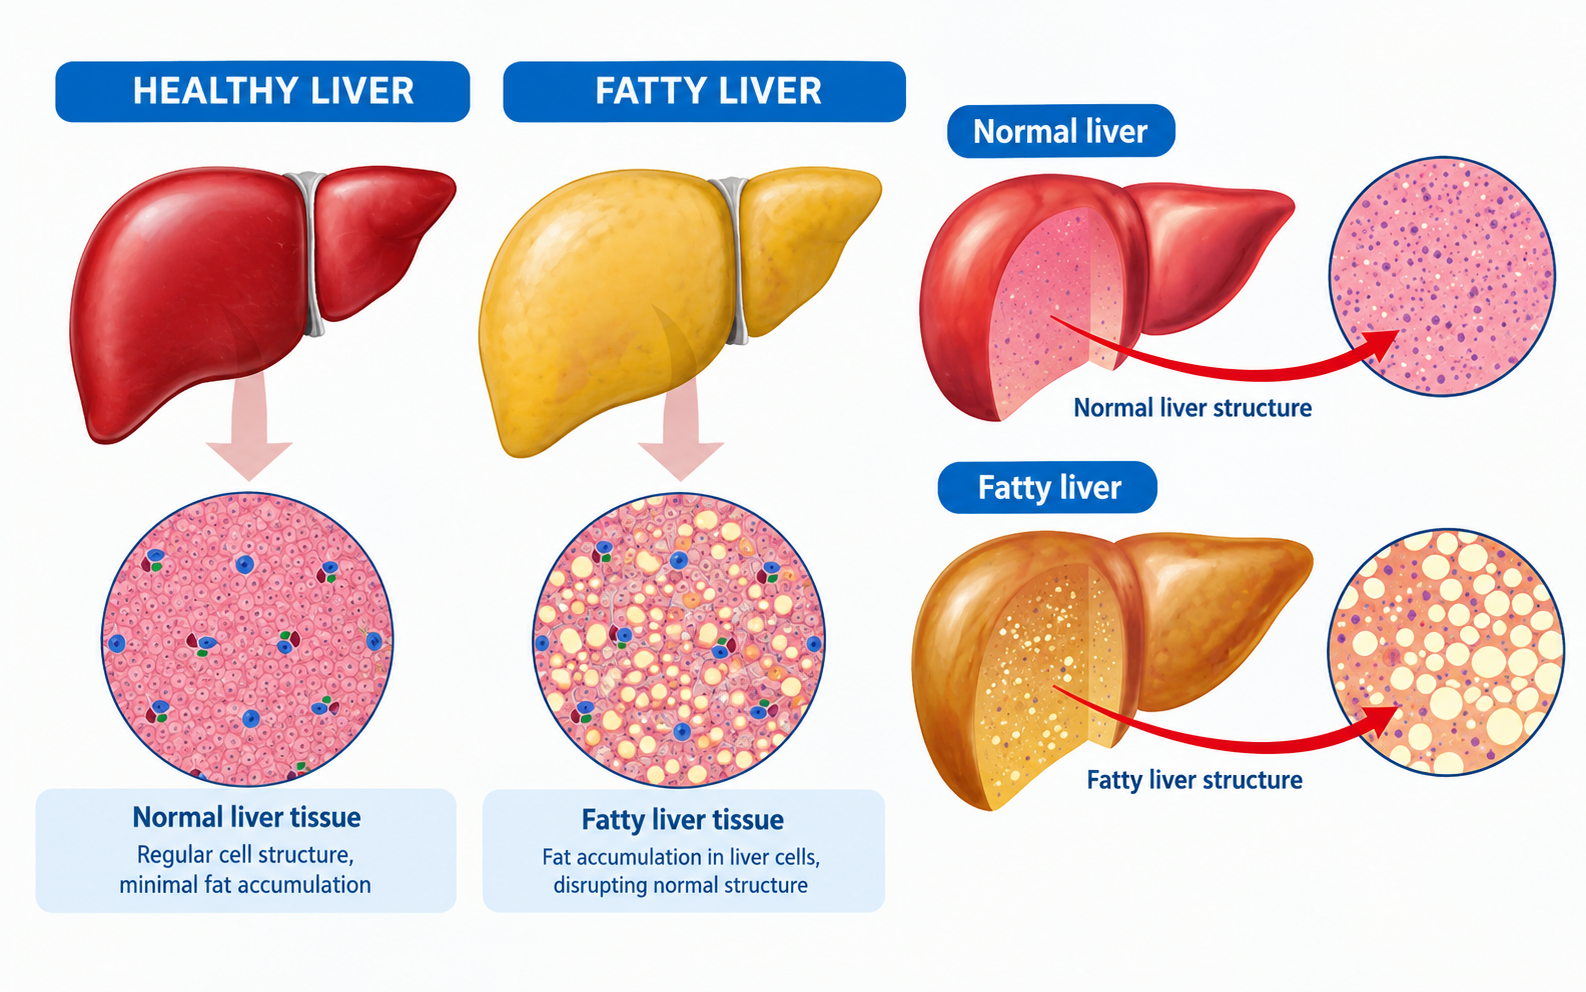
Metabolic fatty liver disease
Insulin resistance increases fat synthesis in the liver and disrupts glucose metabolism. This raises the risk of fatty liver disease, elevated liver enzymes and steatohepatitis in some patients.
People with obesity-related insulin resistance should have liver enzymes checked and undergo liver ultrasound, especially if they have elevated triglycerides or consume alcohol.
Metabolic syndrome
Metabolic syndrome is a cluster of risk factors that includes abdominal obesity, hypertension, elevated blood glucose, high triglycerides and low HDL cholesterol. Insulin resistance is a central mechanism in many cases.
If two to three or more abnormal factors are present, patients should undergo comprehensive assessment of cardiovascular and diabetes risk.
Cardiovascular disease
Insulin resistance is often accompanied by dyslipidemia, hypertension, chronic inflammation and elevated blood glucose. These factors increase the risk of atherosclerosis, coronary artery disease and stroke.
People with obesity-related insulin resistance should not monitor blood glucose alone, but also have their blood pressure, blood lipid profile and cardiovascular risk assessed.
PMOS/PCOS and reproductive disorders in women
Insulin resistance can increase androgen levels in women with PMOS/PCOS, leading to ovulatory dysfunction, infrequent menstruation, acne, hirsutism and difficulty conceiving.
Treatment of PMOS/PCOS in women with obesity often requires simultaneous management of body weight, insulin resistance, nutrition, physical activity and reproductive endocrine health.
How should people with obesity be evaluated for insulin resistance?
There is no single test that is appropriate for everyone. Physicians will determine the necessary tests based on symptoms, BMI, waist circumference, family history, underlying medical conditions and treatment goals.
Note: Fasting insulin and HOMA-IR may support assessment in certain cases, but they are not mandatory tests for everyone with obesity. These indices do not have a universally standardized cutoff for all populations and should be interpreted by a physician together with blood glucose, HbA1c, waist circumference, lipid profile, fatty liver status and underlying medical conditions.
Who is more likely to develop insulin resistance with obesity?
People with abdominal obesity and large waist circumference
Visceral fat is more strongly associated with insulin resistance than subcutaneous fat. People with a “large abdomen” even if their body weight is not very high, should still have their metabolic risk assessed.
People with a family history of type 2 diabetes
Genetics affects insulin secretion capacity and insulin sensitivity. If a family member has diabetes, the risk is higher when obesity is also present.
People who are physically inactive or sit for prolonged periods
Inactive skeletal muscle uses glucose less effectively. Prolonged sitting also reduces energy expenditure, increases abdominal fat and worsens insulin resistance.
People with fatty liver disease or elevated triglycerides
These are signs of metabolic dysfunction that often occur alongside insulin resistance. Patients should have their liver, blood lipid profile and blood glucose assessed.
Women with PMOS/PCOS
PMOS/PCOS is often associated with insulin resistance, especially when abdominal obesity is present. Suggestive signs include infrequent menstruation, acne, hirsutism and difficulty conceiving.
People with insufficient sleep or prolonged stress
Sleep deprivation and stress increase appetite, late-night eating, cortisol dysregulation and blood glucose disturbances. These factors are often overlooked in the treatment of insulin resistance.
People with a history of gestational diabetes
This group has a higher risk of developing type 2 diabetes later in life, especially when postpartum weight gain or abdominal obesity occurs.

Can weight loss improve insulin resistance?
Yes. Appropriate weight loss, especially reducing visceral fat and increasing physical activity, can improve insulin sensitivity. However, the goal is not rapid weight loss, but fat loss, muscle preservation and improvement in metabolic indicators.
Losing 5–10% of body weight may provide metabolic benefits
For people with overweight or obesity, losing a portion of their initial body weight can help reduce visceral fat and improve blood glucose, blood pressure, triglycerides and fatty liver disease.
For example, a person who weighs 80 kg may already experience meaningful metabolic improvement after safely losing 4–8 kg, instead of needing to reach an “ideal weight” immediately.
Preserving muscle helps improve glucose utilization
Skeletal muscle is an important site of glucose uptake. If weight loss occurs too rapidly and causes significant muscle loss, blood glucose control may not improve as expected.
Patients should combine adequate protein intake with strength training, rather than relying only on dieting or cardio exercise.
Avoid extreme weight-loss methods
Prolonged fasting, completely eliminating an entire food group, using weight-loss drugs of unknown origin or misusing diuretics can cause muscle loss, electrolyte disturbances, hypoglycemia or liver and kidney complications.
People with prediabetes, type 2 diabetes, kidney disease, liver disease or cardiovascular disease, or those currently taking medications, should consult a physician before starting an intensive weight-loss regimen.

How to improve insulin resistance in people with obesity
Reduce sugary beverages and refined carbohydrates
Soft drinks, milk tea, sweets, large portions of rice/noodles/vermicelli and sugar-rich snacks can cause marked blood glucose fluctuations. This forces the pancreas to secrete more insulin.
Patients should prioritize plain water and unsweetened tea, reduce sugary beverages and choose slower-digesting carbohydrates such as sweet potatoes, oats and brown rice in appropriate portions, unless contraindicated.
Increase protein and fiber in meals
Protein and fiber help increase satiety, reduce snacking and make meals more stable in terms of blood glucose response. This is an important foundation for patients who want to lose weight while improving insulin resistance.
Each meal should include a protein source such as fish, eggs, lean meat, tofu or unsweetened yogurt, along with green vegetables and whole fruits instead of fruit juice.

Combine aerobic exercise with strength training
Brisk walking, cycling and swimming help increase energy expenditure, while strength training helps skeletal muscle use glucose more effectively. Combining both is often more effective than dieting alone.
Beginners may start with 20–30 minutes of walking per day and strength training 2–3 sessions per week using light weights, resistance bands or bodyweight exercises.
Reduce prolonged sitting time
Even with regular exercise, sitting continuously for many hours still reduces muscle activity. Standing up and walking briefly every 45–60 minutes may help support postprandial blood glucose control.
Patients can take a gentle 10–15-minute walk after meals, use the stairs when appropriate and gradually increase their daily step count.
Get enough sleep and manage stress
Insufficient sleep and prolonged stress increase food cravings, emotional eating and dysregulation of hunger and satiety hormones, making blood glucose more difficult to stabilize.
Patients should try to maintain a consistent sleep schedule, limit screen time before bed, reduce caffeine intake in the late afternoon and evening, and use appropriate relaxation strategies such as walking, deep breathing or light meditation.

Treat underlying conditions and use medication when indicated
Certain medications, such as metformin, diabetes medications or GLP-1 receptor agonists used to support weight management, may be considered by a physician in specific cases, such as high-risk prediabetes, type 2 diabetes, PMOS/PCOS, obesity with metabolic complications or difficulty losing weight through lifestyle measures alone.
Patients should not buy medications on their own, reuse another person’s prescription or take medications based on advertisements. Before initiating treatment, the physician needs to assess BMI, waist circumference, blood glucose, HbA1c, liver and kidney function, underlying medical conditions and current medications.
When should you seek medical care for obesity-related insulin resistance?
You should seek medical evaluation if any of the following situations apply:
Abdominal obesity, with waist circumference of 90 cm or greater in men or 80 cm or greater in women
This may suggest central obesity and increased visceral fat. Patients should have their blood glucose, HbA1c, blood lipid profile and liver status assessed.
Abnormal fasting blood glucose, HbA1c or blood insulin
These indicators may suggest prediabetes, type 2 diabetes or compensatory hyperinsulinemia. A physician should interpret the results and develop an appropriate monitoring plan.
Fatty liver disease, elevated triglycerides or elevated liver enzymes
These metabolic disorders often occur alongside insulin resistance. A comprehensive assessment of the liver, blood glucose and lipid profile is needed.
Sleepiness after meals, rapid hunger, sweet cravings or difficulty losing weight
These signs do not diagnose insulin resistance, but if they recur in people with obesity or abdominal obesity, metabolic evaluation should be considered.
Infrequent menstruation, acne, hirsutism or difficulty conceiving in women
These signs may be associated with PMOS/PCOS and insulin resistance. Coordination between endocrinology and obstetrics-gynecology may be needed.
Repeated weight-loss attempts followed by weight regain
Patients need assessment of dietary intake, physical activity, muscle mass, sleep, stress, current medications and underlying metabolic conditions.
Seek medical care or emergency treatment promptly if abnormal signs occur
Medical care or emergency treatment is needed if any of the following signs appear:
- marked excessive thirst and frequent urination;
- rapid unexplained weight loss;
- extreme fatigue or altered consciousness;
- persistent vomiting or inability to eat or drink;
- chest pain or shortness of breath;
- very high blood glucose if home glucose monitoring is available;
- signs of dehydration or severe infection.
At the Obesity Management Center, Hong Ngoc General Hospital, patients have access to a multidisciplinary assessment model involving endocrinology, nutrition, gastroenterology, oncology and other relevant specialties to develop a comprehensive weight management and disease screening strategy. This multidisciplinary approach helps evaluate insulin resistance in the context of body weight, waist circumference, blood glucose, fatty liver disease and cardiovascular risk. Patients may contact the hotline at 024 3927 5568 or leave their information in the form to be contacted by healthcare staff for consultation.
Frequently asked questions
Can obesity cause insulin resistance?
Yes. Obesity, especially abdominal obesity and visceral fat, increases free fatty acids, chronic inflammation and impaired insulin signaling in the liver, skeletal muscle and adipose tissue. This makes the body respond less effectively to insulin and increases the risk of prediabetes and type 2 diabetes.
Is insulin resistance the same as diabetes?
No. Insulin resistance is a condition in which the body responds poorly to insulin. Blood glucose may remain normal in the early stages because the pancreas increases insulin secretion to compensate. If prolonged, insulin resistance can lead to prediabetes or type 2 diabetes.
What are the signs of insulin resistance in people with obesity?
Insulin resistance often has no specific symptoms. Suggestive signs include abdominal obesity, acanthosis nigricans on the neck or underarms, sleepiness after a high-carbohydrate meal, fatty liver disease, elevated triglycerides, increased HbA1c or menstrual irregularities, acne and hirsutism in women.
Can insulin resistance cause weight gain?
It may contribute to weight gain. Insulin resistance causes the pancreas to secrete more insulin, which may make the body more likely to store energy in the setting of excess calorie intake and physical inactivity. However, weight gain also depends on diet, physical activity, sleep, stress, medications and underlying medical conditions.
Which tests can detect insulin resistance?
A physician may order fasting blood glucose, HbA1c, fasting insulin, HOMA-IR, blood lipid profile, liver enzymes and liver ultrasound. Patients should not interpret blood insulin or HOMA-IR results in isolation, as these results need to be assessed in the clinical context.
Does a high HOMA-IR definitely mean disease?
No conclusion can be made based on HOMA-IR alone. This index may support the assessment of insulin resistance in certain cases, but there is no single cutoff that applies uniformly to everyone. Results should be interpreted by a physician together with symptoms, blood glucose, HbA1c, waist circumference, lipid profile, liver status and underlying medical conditions.
Can weight loss resolve insulin resistance?
Appropriate weight loss, especially reducing visceral fat, can improve insulin sensitivity. However, the degree of improvement varies from person to person and depends on physical activity, nutrition, sleep, underlying medical conditions and medications, if any.
Do people with insulin resistance need medication?
Not everyone needs medication. Some people can improve insulin resistance through weight loss, nutrition, physical activity and adequate sleep. If prediabetes, type 2 diabetes, PMOS/PCOS or high metabolic risk is present, a physician may consider appropriate medication.
How is PMOS/PCOS related to insulin resistance?
PMOS, previously commonly referred to as PCOS, may be associated with insulin resistance and elevated androgen levels. This can cause infrequent menstruation, acne, hirsutism, ovulatory dysfunction and difficulty conceiving. Patients should be evaluated for both reproductive endocrine and metabolic health.
Conclusion
Obesity and insulin resistance have a bidirectional relationship. Visceral fat, chronic inflammation, fatty liver disease, physical inactivity and sleep disturbances can make the body less responsive to insulin. If prolonged, this condition increases the risk of prediabetes, type 2 diabetes, metabolic syndrome, fatty liver disease, PMOS/PCOS and cardiovascular disease.
If abdominal obesity, difficulty losing weight, abnormal blood glucose or HbA1c, fatty liver disease, elevated triglycerides or signs suggestive of PMOS/PCOS are present, patients should see an endocrinologist for insulin resistance risk assessment and an appropriate management plan.
References